Doctors & patients are saying about 'A-Fib.com'...
"A-Fib.com is a great web site for patients, that is unequaled by anything else out there."
Dr. Douglas L. Packer, MD, FHRS, Mayo Clinic, Rochester, MN
"Jill and I put you and your work in our prayers every night. What you do to help people through this [A-Fib] process is really incredible."
Jill and Steve Douglas, East Troy, WI
“I really appreciate all the information on your website as it allows me to be a better informed patient and to know what questions to ask my EP.
Faye Spencer, Boise, ID, April 2017
“I think your site has helped a lot of patients.”Dr. Hugh G. Calkins, MD Johns Hopkins,
Baltimore, MD

A-Fib Related Strokes & Answers to Your Top 5 Questions

 Several research studies have compared A-Fib patients who have had an ischemic stroke against stroke patients who did not have A-Fib.
A-Fib Strokes By Comparison
A-Fib stroke patients were associated with more widespread deprivation of blood supply to the brain, more extensive growth of dead tissue areas (from failure of blood supply), more rapid and severe deterioration, and higher mortality rate. In addition, outcomes were worse for A-Fib stroke patients with a longer duration of their Atrial Fibrillation.
Why Are A-Fib Stroke More Severe?
A-Fib strokes may be worse because of the larger size of the clots. Most (95%) of A-Fib strokes originate with clots from the Left Atrial Appendage (LAA). Clots that form in the LAA can be quite large and completely block blood vessels in the brain often resulting in death or severe neurologic damage.
A-Fib Related Strokes: Answers to Your Top 5 Questions
Since we started publishing A-Fib.com, we have answered thousands of patient’s questions—perhaps the same questions you may have right now. Here we share answers to your top 5 questions asked about stroke risk and anticoagulation (click the link to read the answer).
1. “What are my chances of getting an A-Fib stroke?“
2. “If a clot causes a stroke, what difference does it make if it comes from A-Fib or other causes? Isn’t the damage the same?“
3. “I have infrequent episodes of A-Fib. Do I have to be on a blood thinner?”
4. “Are there alternatives to taking anticoagulants? “My heart doctor wants me to take Xarelto. I am concerned about the side effects. What else can I do?”
Related question: “Is there a way to get off blood thinners all together? I hate taking an anticoagulant. I know I’m at risk of an A-Fib stroke.”
Options for A-Fib Stroke Prevention: Beyond Drug Therapy
A-Fib patients have several options to prevent A-Fib strokes rather than having to take a Direct Oral Anticoagulant (DOAC) such as Apixaban (Eliquis) or Rivaroxaban (Xarelto).
1. The most obvious one is to become A-Fib free through a catheter ablation. You can’t have an A-Fib stroke if you no longer have A-Fib. To learn more, see Catheter Ablation For Atrial Fibrillation (Pulmonary Vein Ablation/Isolation)
2. Another option is to close off or cut out the Left Atrial Appendage (LAA) where most A-Fib clots originate (strategies include the Watchman and Amulet occlusion devices or AtriClip heart surgery). To learn more, see Left Atrial Appendage Closure (LAAC) for A-Fib: The Watchman Works!
3. A third option is a natural blood thinner. Ask your doctor about your CHA2DS2-VASc score (a stroke risk assessor). If your score is a 1 or 2 (out of 10), ask if you could take a non-prescription approach to a blood thinner such as turmeric, ginger and vitamin E or, especially, the supplement Nattokinase, a powerful fibrinolytic enzyme that helps dissolve fibrin, the tough protein web that binds blood clots together. To learn more, see “Are natural blood thinners as good as prescription blood thinners?”
If you find any errors on this page, email us. Y
Last updated: Monday, September 28, 2026
Return to Frequently Asked Questions
Watchman Occlusion Device – Blood Thinners Alternative
The Watchman™ Device: An Alternative to Blood Thinners

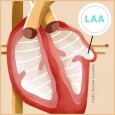
 Illustration of the Left Atrial Appendage (LAA) in the Left Atrium
By Steve S. Ryan, PhD, Last updated: September 4, 2026
Do you hate having to take an anticoagulant? Hate the side effects? A replacement for taking blood thinners is an occlusion device such as the Watchman from Boston Scientific.
It’s known that 90%-95% of A-Fib related clots originate in a small pouch at the top of the heart called the Left Atrial Appendage (LAA). The Watchman is a one-time, minimally invasive heart implant used to close off the LAA to reduce stroke risk in people with atrial fibrillation.

 Watchman barbs
The very low risk procedure takes about 30 minutes under general anesthesia, and most patients go home within a day. Afterwards you usually do not need to be on an anticoagulant.
It has been used to treat more than 100,000 patients worldwide. Some patients with challenging heart anatomies, such as a shallow appendage, may not be good candidates for the procedure.
The Watchman Procedure
The Watchman device comes in multiple sizes to accommodate the different shapes of LAAs. Once a patient’s Left Atrial Appendage is measured, a wide-sheathed catheter with a spline is used to insert the Watchman device which has a self-expanding open-ended circular frame.

 Illustration: Watchman placement in LAA
The atrial surface of this frame is covered with a thin, permeable 160 μm (micron) pore filter made of polyester material. This filter allows blood to pass through while stopping clots. Little hooks or anchors called fixation barbs at the middle of the device make sure it is attached firmly to the LAA wall.
Before the catheter is removed (which fixes the Watchman in place), contrast agents are used to make sure the Watchman is stable and closes off the LAA opening.
Over time heart tissue grows over the polyester (PET) material so that it completely closes off the LAA with smooth heart tissue similar to other heart surfaces.
After Watchman Installation

 Watchmen anatomical view 9 months after install (autopsy image of patient who died from non-heart related causes.)
Patients continue on their anticoagulant for several weeks after the Watchman device is inserted.
They are then examined using a Transesophageal Echocardiogram (TEE) to make sure there is complete closure of the LAA. At that time your doctor with determine if and how long you should continue on your anticoagulant.
You can think of the Watchman as a replacement for blood thinners. Both reduce but do not totally eliminate the risk of stroke. The stroke risk is reduced to that of a person with a normal heart.
Catheter Ablation + Watchman Concomitant Procedure
Many patients today undergoing a catheter ablation are also having a Watchman device installed, often in the same procedure.
The catheter ablation treats the source of A-Fib while the Watchman device reduces A-Fib-related stroke risk, eliminating the need for lifelong blood thinners.
 The OPTION randomized controlled clinical trial concluded in 2025 after 3-years of follow-up. It found for people who had both procedures at the same time, getting an ablation and Watchman implant was just as safe as getting an ablation alone.
After an ablation, the Watchman implant was shown to be just as safe as blood thinners and just as effective at reducing stroke risk – plus, people with the Watchman were 50% less likely to have a bleeding event.
Is There a Watchman or a Concomitant Procedure in Your Future?
If don’t want to be on an anticoagulant, consider having your Left Atrial Appendage closed off to keep A-Fib related clots from escaping and causing a stroke. If you are considering a catheter ablation to cure your A-Fib, ask your Electrophysiologist about having a concomitant procedure—a two-for-one procedure.
To learn more about the Watchman device, watch a video of the Watchman being installed.
VIDEO: Placement of the Watchman FLX™ Left Atrial Appendage Closure Device. Illustrates insertion of the Watchman FLX™ by a catheter through the groin to the heart and positioning to close off the Left Atrial Appendage; Narration, illustrations and animation. (1:58 min.) Go to video->

Return to Article Index: Drug Therapies and Medicines
If you find any errors on this page, email us. Y Last updated: Friday, September 4, 2026
2025 AF Symposium: Real-World Problems of Stroke Patients with A-Fib

After a short hiatus, I’ve finished another report from the 2025 AF Symposium.
During the Symposium’s Thursday afternoon session, Dr. Dhanunjaya Likkireddy of the Kansas City Heart Institute, Overland Park, KS, described the predicament and challenges of Atrial Fibrillation patients who suffer a stroke.
He noted how after discharge, A-Fib patients who survive a stroke often don’t have follow-up with a neurologist [a specialist who treats disorders including stroke]. The result? “They lose their job, their friends, their family and they ultimately die.”
 Dr. Likkireddy pointed out that stroke is the number one cause of disability and the fifth leading cause of death in the U.S. The Kansas City Heart Institute found that more than 70 percent of these stroke victims experience some form of disability.
Functional recovery after stroke is an important part of restoring people’s lives. Dr. Likkireddy went on to describe the insightful findings of the RESCUE-STROKE Pilot Study.
This study gives new hope to these unfortunate patients suffering with both stroke and Atrial Fibrillation. According to Dr. Lakkireddy “it gives them an opportunity for a meaningful recovery.”
Continue reading about the findings of the RESCUE-STROKE Pilot Study and what it means to A-Fib patients who suffer a stroke. Go to my report.
2025 AF Symposium: Real-World Problems of Stroke Patients with Atrial Fibrillation
2025 AF Symposium

 Dhanunjaya Likkireddy MD
Real-World Problems of Stroke Patients with Atrial Fibrillation
One presenter during the Thursday afternoon’s “Late Breaking Clinical Science Session II” was Dr. Dhanunjaya Likkireddy of the Kansas City Heart Institute, Overland Park, KS.
Dr. Likkireddy described the predicament and challenges for Atrial Fibrillation patients who suffer a stroke.
After discharge, they often don’t have follow-up with a neurologist [a specialist who treats disorders including stroke]. “They lose their job, their friends, their family and they ultimately die.”
The Sober Facts About Stroke
Dr. Likkireddy pointed out that stroke is the number one cause of disability and the fifth leading cause of death in the U.S.
Strokes are either ischemic [blood clots which block blood flow] or hemorrhagic [bleeding in the brain].
Eighty percent of strokes are ischemic. Within 6 months, 20% of stroke victims experience repeated strokes. Recurring hospitalizations are common.
Atrial Fibrillation is an important risk factor for stroke and accounts for 25% of ischemic strokes.
The Kansas City Heart Institute found that more than 70 percent of these stroke victims experience some form of disability.
Yet Widely Inadequate Management After Stroke
Functional recovery after stroke is an important part of restoring people’s lives.
– Dr. Dhanunjaya Lakireddy
Inadequate management after stroke is widely prevalent. In Dr. Lakireddy’s words, there’s a “therapeutic black hole of A-Fib and stroke management.
This is something we should be able to really pick up on by making simple tweaks to their management.”
RESCUE-STROKE Pilot Study
Dr. Likkireddy described the RESCUE-STOKE study that looked at A-Fib patients who survived a stroke and the impact of subsequent treatments, i.e., Catheter Ablation versus conventional drug treatment.
In this small pilot study, researchers performed a retrospective, observational study of patients hospitalized with stroke and new-onset A-Fib from 2021 to 2023. They created two different study groups of stroke survivors who were diagnosed with A-Fib at the time of their stroke. (Anyone with a hemorrhagic stroke was excluded from the study.)
The first group had treatment with catheter ablation aimed at restoring and maintaining normal sinus rhythm. The second employed routine drug management (oral anticoagulants, antiarrhythmic drugs). Each group contained 36 patients for a total study population of 72.
Researchers followed the study patients for 12 months. They also collected data using loop recorders. They incorporated the results in a Modified Rankin Scale.
Study Results
Dramatic differences were found between the Catheter Ablation group and the Drug Management group. The Catheter Ablation group findings were significantly better including:
1. The number of repeat strokes decreased considerably (25% vs 8.3%).
2. Major bleeding decreased (25% vs 11%).
3. A-Fib-related hospitalizations decreased in a major way (69.4% vs 25.0%).
4. And most importantly, cumulative cardiovascular outcomes showed a major improvement (78.6% vs 25.0%).

 Graphic: Early Catheter Ablation for Incident Atrial Fibrillation Post-Stroke Appears Associated With Improved Outcomes (RESCUE-STROKE)
In other words: Those that underwent Catheter Ablation reached rhythm control faster, with continued A-Fib freedom at 12 months; had fewer repeat strokes; and less major bleeding, number of hospitalizations, and mortality.
In Dr. Lakkireddy’s words, the Catheter Ablation group was significantly better “by a huge score”. The Catheter ablation group of patients benefited from early intervention, more directed care, and guided therapy.
Researchers Note: Because of important differences in the study populations, additional studies are needed.
Editor’s Comments
 Editor’s Comments
This study gives new hope to these unfortunate patients with both stroke and Atrial Fibrillation. According to Dr. Lakkireddy “it gives them an opportunity for a meaningful recovery.”
Stroke Survivors at Great Risk: Survivors of a stroke who also have or develop A-Fib are in a difficult situation (vs. A-Fib patients without stroke). Most have experienced some form of disability (70%). In addition, 20% of stroke survivors will have another stroke within 6 months.Early intervention with catheter ablation results in significant improvement in neurological outcomes, adverse events, and A-Fib-related outcomes.
For stroke survivors, A-Fib adds to their stroke risk. Dr. Lakkireddy paints a grim picture of their future. “They lose their jobs, their friends, their family, and they ultimately die.”
There is Real Hope for Stroke Survivors with A-Fib: The key is early intervention with catheter ablation which results in significant improvement in neurological outcomes, adverse events, and A-Fib-related outcomes.
Patients with early intervention had a faster time to rhythm control, continued freedom from A-Fib at 12 months, fewer repeat strokes, less major bleeding, less hospitalizations, and a major improvement in mortality (0% vs 11.1%).
We patients are most grateful to Dr. Lakkireddy and his colleagues for the hope he has provided to stroke survivors with A-Fib who often have a challenging road to recovery.

Return to 2025 AF Symposium Reports
If you find any errors on this page, email us. Y
Last updated: Monday, September 15, 2025
First-Time Catheter Ablation for Atrial Fibrillation Safer Than Ever

For patients with symptomatic A-Fib, catheter ablation is a commonly performed procedure. However, it does have potential complications. As with any procedure, the informed patient needs to know the risk factors.
To determine the most recent complication rates, researchers did a systematic review and pooled analysis of 89 studies from the past 10 years. Their results were published in May 2023.
Research Methods
EDLINE and EMBASE databases were searched from January 2013 to September 2022 for randomized control trials that included patients undergoing a first ablation procedure using either radiofrequency or cryoballoon.
A total of 89 studies met inclusion criteria. A total of 15,701 patients were included in the current analysis.
Survey Findings
Vascular complications (i.e., bleeding and clotting) were the most frequent type of complication (1.31%).
The next most common complications were pericardial effusion/tamponade  (i.e., fluid buildup around the heart) (0.78%) and stroke/transient ischemic attack (blood clot to the brain) (0.17%).
During the 10-year period of the analysis, procedure-related complication rates were:
• Overall 4.51%
• Severe 2.44%
Comparing the earlier 5-year period to the most recent 5-year period, complication rates were:
• Earlier period: 5.31%
• Most recent period: 3.77%.
Over the 2 time periods, mortality rates were stable.
There was no significant difference as to pattern of A-Fib, ablation technique, or ablation strategies beyond the pulmonary vein isolation.
Researchers Conclusions
Complication rates have declined in the past decade (2013-2022).
A significant improvement in the safety of the procedure was observed over the last 5 years (2018-2022).
Neither the type of energy used for ablation nor the creation of additional lesions in addition to the pulmonary veins significantly influenced the procedural complication rate.
What This Means for A-Fib Patients
One of the drawbacks of these findings from a patient’s perspective it that it doesn’t differentiate between major and minor complications.
All Complications Are Not Equal: For example, vascular complications (such as bruising or bleeding at the catheter insertion points) are usually minor and easily taken care of with no lasting consequences.
More serious complications are:
• Tamponade: Blood can bleed into the pericardium sac that surrounds the heart compressing it. Most centers and Electrophysiologists (EPs) are well aware of this and can move swiftly to drain off the extra blood.
• Atrioesophageal Fistula: This is a very rare complication (less than 1 in 1000) but one which can kill you. When a catheter makes an RF burn (lesion) near the esophagus, the heat may damage the esophagus wall which can later be eroded by gastric acids allowing blood to leak into the esophagus. Most centers and EPs now take extensive precautions to prevent this. (The new technology, Pulse Field Ablation, virtually eliminates this complication, see Pulsed Field Ablation—Emerging Tech for Atrial Fibrillation)
• Stroke: During a catheter ablation you are on heavy-duty anticoagulants so strokes are rare (0.17%). But as with anyone with A-Fib, strokes can occur.
In this analysis of 89 studies the overall major complication rate was very small.
First-Time Catheter Ablation: The bottom line for us patients is that first-time catheter ablation (PVA) is one of the safest procedures you can have in a hospital. (FYI: By comparison, the complication rate for the common appendectomy is around 18%.)
In practice, for most A-Fib patients, the actual risks are so small that it’s safer getting a PVA than not getting one.
A PVA is safe and afterwards certainly feels a lot better than a life in A-Fib and/or a life on antiarrhythmic drugs and anticoagulants. One reason people get a PVA is so that they don’t have to live the rest of their lives on these drugs.
Catheter Ablation is Considered a Low-Risk Procedure: Over 1 million catheter ablations are performed annually in the U.S.
The complication rate has continued to decrease. In this analysis a significant improvement in safety was observed over the last 5 years.
But Beware of Low-Volume Operators: As patients we need to be aware that complications come mostly from low volume operators (those who perform less than 25 ablations a year), and that 81% of all ablations are performed by low volume operators.
This is important! When choosing to have a catheter ablation, make the effort to find high volume operators and experienced hospitals.

Bleeding From Anticoagulants—All Anticoagulants are Dangerous

No one likes to take anticoagulants. They are inherently dangerous.
Drug therapy with oral anticoagulants in patients with atrial fibrillation is based on finding the ideal balance of effectiveness versus safety of these drugs.
In real-world clinical practice, bleedings were the most typical and common adverse events from treatment with oral anticoagulants (NOACs). Data from observational studies are an additional source of information for the adverse events (AEs) that come from taking anticoagulants.
The incidence of bleeding of those treated with NOACs was approximately 8% to 9%. (The bleeding risk with warfarin, was much higher.)
How Anticoagulants Decrease Your Risk of Blood Clots and Stroke
To decrease your risk of blood clots and stroke, anticoagulants hinder the clotting ability of your blood. The result is anticoagulants can cause or increase bleeding. That’s how they work.
In addition, they increase your risk of microbleeds in the brain, hemorrhagic stroke, early dementia, and gastrointestinal bleeding.
“Oral anticoagulants are high-risk medications” (Drs. Witt & Hansen).
Alert to Anyone Taking Anticoagulants
This study from Russia is another Red Flag alert for anyone taking anticoagulants.
It’s like playing Russian Roulette with your health. One out of ten times you’re at risk of a bullet to the brain (i.e., 8%-9% risk of Adverse Events when taking anticoagulants).
None the Less, Anticoagulants Do Reduce Your Chance of Stroke
But in spite of the possible negative effects of anticoagulants, if you have A-Fib and are at real risk of stroke, anticoagulants do work.
You’re no longer 4–5 times more likely to have an A-Fib (ischemic) stroke. Taking an anticoagulant to prevent an A-Fib stroke also may give you peace of mind.
If You Have A-Fib, Can You Safely Stop Taking Anticoagulants?
Never just stop taking your anticoagulant or reducing the dosage. That’s a decision for you and your doctor.
Yes! The best way to deal with the increased risk of stroke and side effects of anticoagulants is to no longer need them.
Here are three options:
#1 Alternative: Get rid of your A-Fib
As EP and prolific blogger Dr. John Mandrola wrote: “…if there is no A-Fib, there is no benefit from anticoagulation.”
Action: Request a catheter ablation procedure. Today, you can have an ablation immediately (called ‘first-line therapy’). You don’t have to waste a year on failed drug therapies. See Catheter Ablation Reduces Stroke Risk Even for Higher Risk Patients
#2 Alternative: Close off your Left Atrial Appendage (LAA)
The Left Atrial Appendage is where 90%-95% of A-Fib clots originate. Close off your LAA and you may no longer need to take an anticoagulant.
Action: Request a Watchman occlusion device. The Watchman device is inserted to close off your LAA and keep clots from entering your blood stream. See Watchman Better Than Lifetime on Warfarin
#3 Alternative: Consider non-prescription blood thinners
Ask your doctor about your CHA2DS2-VASc score (a stroke risk assessor). If your score is a 1 or 2 (out of 10), you are at low risk of having a stroke. You may not need to take an anticoagulant at all.
Action: Ask your doctor if you could take a non-prescription approach to a blood thinner. Perhaps you can benefit from an increase in natural blood thinners such as turmeric, ginger, vitamin E or, especially, the supplement Nattokinase. See FAQ: “Are natural blood thinners as good as prescription blood thinners?” (Only change your medication under your doctor’s supervision.)
What this Means for A-Fib Patients
Bleeding from taking anticoagulants is a serious side effect. Drug therapy with oral anticoagulants is based on finding the ideal balance of effectiveness versus safety of these drugs.
Perhaps the best balance may be to avoid needing anticoagulants in the first place:
Your options: Seek your A-Fib cure, i.e., get rid of your Atrial Fibrillation. Reduce your risk of stroke by closing off your Left Atrial Appendage. Or seek a non-drug natural blood thinner option to taking an anticoagulant.

A-Fib Patients Study: After Brain Hemorrhage, Back on Anticoagulation?

Sometimes I just can’t understand some of the research studies done about Atrial Fibrillation such as this one. I can not wrap my head around this recent study from the Netherlands (APACHE-AF).
They studied A-Fib patients who survived intracerebral hemorrhage after being treated with anticoagulation for atrial fibrillation. Their hemorrhagic stroke was “anticoagulant-associated”. Seven to 90 days after their hemorrhage, patients were either put back on anticoagulation (50 patients) or avoided anticoagulation.
WHAT?! How can you put someone back on an anticoagulant which probably caused their hemorrhagic stroke in the first place?
These researchers certainly knew the alternative options to taking anticoagulants.
This study was done at 16 hospitals in the Netherlands but was nevertheless very small. Most patients who did suffer a hemorrhagic stroke either died or were severely disabled. Few survived. That’s why there were so few patients in the study.
Further Damage From Anticoagulation
Not surprisingly, after a minimum follow-up of 6 months (a very short follow-up), 26% of the apixaban group had non-fatal strokes or vascular death. The patients on antiplatelet therapy (26) or no anticoagulation didn’t do very well either.
The researchers themselves concluded, “Patients with atrial fibrillation who had an intracerebral hemorrhage while taking anticoagulants have a high subsequent annual risk of non-fatal stroke or vascular death.”
Did I Miss Something?
How can you put someone back on an anticoagulant, even Eliquis, when anticoagulants probably caused their hemorrhagic stroke in the first place? This seems both ethically wrong and wrong-headed.
Did I miss something important? If anyone wants to share their view of this study with me, send me an email.
2022 AF Symposium: Procedural Anticoagulation with LAA Closure Devices for A-Fib Patients

In this report from the 2022 AF Symposium, Dr. Luigi Di Biase of the Albert Einstein College of Medicine, Bronx, NY gave a presentation on “Peri and Post Procedural Anticoagulation with LAA Closure Devices―An Evolving Story”.
In particular, he is talking about the Watchman occlusion device to close off an A-Fib patient’s Left Atrial Appendage. His focus is on the anticoagulation protocol following the procedure involving, that is, the drug regime for patients in the months afterward. e.g., DOACs, aspirin and clopidogrel.
This is a short report, a quick read, go to Procedural Anticoagulation with LAA Closure Devices―An Evolving A-Fib Story.

(Finally) A Head-to-Head Comparison of Anticoagulants for A-Fib: Eliquis vs Xarelto

The most commonly prescribed direct-acting anticoagulants (DOACs) for A-Fib patients are Eliquis (generic name: apixaban) and Xarelto (generic name: rivaroxaban).
Direct-acting anticoagulants (DOACs) were introduced in the early 2010s, but most of the testing has been against warfarin, not against other DOACs. Finally, thanks to the researchers of two retrospective studies, A-Fib patients now have a head-to-head comparison of Eliquis versus Xarelto.
Study 1: Stroke and Bleeding Risks
A recent retrospective study (Fralick, M. et al) looked at 6 years of prescription data for atrial fibrillation patients from the Nationwide Healthcare Claims Database (NPIC). A-Fib patient group sizes were matched (39,351 each). Mean age was 69 years, 40% were women and follow up was 288–291 days.
Significant Findings
1. Eliquis patients had significantly lower rates of stroke or systemic embolism (6.6 vs 8.0 events per 1000 person-years) compared to Xarelto.
2. Eliquis patients had a significantly lower incidence of major bleeding, defined as gastrointestinal bleeding or intracranial hemorrhage (12.9 vs 21.9 events per 1000 person-years).
Researchers Conclusion (Fralick, M. et al): In routine care, adults with atrial fibrillation prescribed apixaban had a lower rate of both ischemic stroke or systemic embolism and bleeding compared with those prescribed rivaroxaban.
Study 2: Stroke and Bleeding Risks
A second retrospective study (Ray, W. et al) looked at 581,451 atrial fibrillation patients 65 years or older who were enrolled in Medicare from 2013–2018. A-Fib patient group sizes were Rivaroxaban, 227,572 and Apixaban, 353,879. Follow up was for 4 years, through November 30, 2018. Mean age was 77.0 years; 50.2% were women (291 966).
Significant Findings
1. Xarelto patients had more hemorrhagic events including fatal extracranial bleeding (1.4 vs 1.0 per 1000 person-years)
2. Xarelto had more nonfatal extracranial bleeding (39.7 vs 18.5 per 1000 person-years)
3. Xarelto had more fatal ischemic/hemorrhagic events (4.5 vs 3.3 per 1000 person-years)
4. Xarelto had more “total mortality” (44.2 vs 41.0 per 1000 person-years)
Researchers Conclusions and Relevance (Ray, W. et al): Among Medicare beneficiaries 65 years or older with atrial fibrillation, treatment with rivaroxaban compared with apixaban was associated with a significantly increased risk of major ischemic or hemorrhagic events.

Eliquis vs Xarelto…and the Winner is…
Eliquis (apixaban)! In routine care, Eliquis was found to be both more effective and safer than Xarelto.
As patients, we should pay particular attention to the fact that Eliquis had significantly lower incidence of major bleeding (gastrointestinal bleeding or intracranial hemorrhage) than Xarelto (12.9 vs 21.9 events). And that Xarelto had increased nonfatal extracranial bleeding (39.7 vs 18.5 events) compared to Eliquis.
These differences in bleeding weren’t just “statistically significant” but were really alarming. Major, red flag warning important. Particularly for older people who are more prone to bleeding problems.
Be Your Own Best Patient-Advocate
Whether or not to take anticoagulants and which one is one of the most difficult decisions you and your doctor must make.
All the results cited above were “significant” and should be taken into account when choosing an anticoagulant.
If you are taking Xarelto, you should talk with your doctor about switching to Eliquis.
Learn all you can about your health conditions. A well-informed patient is welcomed by your doctors and healthcare caregivers. (If not, consider changing doctors.)
• Dawwas, G.K. et al. Apixaban Versus Rivaroxaban in Patients With Atrial Fibrillation and Valvular Heart Disease—A Population-Based Study. Annals of Internal Medicine, 18 October 2022. https://www.acpjournals.org/doi/10.7326/M22-0318 https://doi.org/10.7326/M22-0318

2022 AF Symposium: The LOOP Study–Implications for Clinical Practice

Last week, I published my Overview of the 2022 AF Symposium held in January in New York City. You can find it on my page, My Summary Reports Written for Atrial Fibrillation Patients.
“The LOOP Study – Implications for Clinical Practice and Future Trials” was presented by Dr. Andrea Russo of Cooper University Hospital in Camden, New Jersey.

 Dr. Andrea Russo
A-Fib Strokes More Dangerous: Dr. Russo described how one-third of strokes are due to A-Fib. And these strokes are more severe and debilitating than those not associated with A-Fib. Many were not diagnosed with Atrial Fibrillation until after they had a stroke or heart attack.
The LOOP Study Research: The researchers posed the questions: Is all A-Fib is worth seeing or worrying over? “Does all detected A-Fib require anticoagulation?” Is A-Fib lasting more than 6 minutes but less than 24 hours duration, really a threat?
From 4 centers in Denmark, study patients received the Medtronic Reveal LINQ LOOP Implantable Recorders (ILR), the Reveal LINQ to investigate…. continue reading The Loop Study.



